INTRODUCTION
The International Association for the Study of Pain (IASP) defines pain as "an unpleasant sensory and emotional experience associated with actual or potential tissue damage, or described in terms of such damage". Two significant types of pain are physiological (acute) and clinical (chronic). Acute pain is a normal physiological reaction to injury that provides an early warning and can help diagnose a problem (e.g., sprain/strain). Without pain, you might seriously hurt yourself without knowing it, or you might not realize you have a medical problem that needs treatment. Most injuries heal within three months. Chronic pain is pain that does not go away after three months. It can be intermittent (occurring on and off) and may vary in intensity during the day, or it can be persistent. Chronic pain can result from a known cause, such as surgery or inflamed joints, or from a disease process, such as rheumatoid arthritis. Before a diagnosis is made for chronic pain, tests may be done to rule out or identify other conditions that can cause pain. These tests may include a neurological exam, orthopedic tests, and a mental health assessment. In most cases, test results are normal, making it difficult to identify the exact cause because the etiology (original cause) is unknown. Chronic pain is abnormal pain processing in which the original injury or cause of acute pain has resolved, but the warning system has failed to shut off. When this occurs, the warning bells keep ringing; however, they no longer signal “danger” or “harm” but instead indicate a pain-processing problem. Chronic pain comes in different forms. Two significant, non-cancer chronic pains are:
1-Musculoskeletal Pain affects the bones, muscles, ligaments, and tendons. It can result from various causes, including sports or occupational injuries, motor vehicle collisions, repetitive strain injuries, and disease processes, such as arthritis.
2-Neuropathic Pain is a complex, multi-faceted state of chronic pain with no apparent cause. It can involve damaged tissue, injury, or malfunctioning nerve fibers or changes in brain processing. An example of neuropathic pain is phantom limb syndrome. The brain still receives signals from nerves that once carried impulses from the now-missing limb. Other types of neuropathic pain include numbness, burning, "pins and needles" sensations, and shooting pain.
BIO-PSYCHO-SOCIAL MODEL
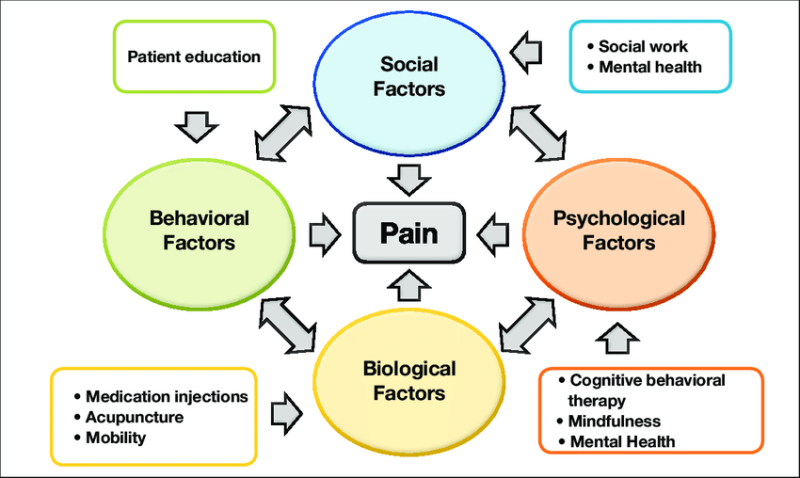
Mild intermittent chronic pain can be treated with drugless, non-invasive methods. Regular exercise, proper posture/body mechanics, adequate sleep, a healthy diet, and complementary therapies such as Chiropractic Manipulative Treatment (CMT), Physical Therapy (PT), Acupuncture/Acupressure, Massage Therapy, and Yoga may help reduce chronic pain by stimulating Endorphin release. In addition, psychological counseling may help the patient cope with the pain and with common reactions they might have to it, such as frustration, fear, anger, depression, and anxiety. Chronic pain can often be successfully managed so that the patient's quality of life significantly improves; however, if the pain persists or becomes more severe, then there is a need for more invasive methods such as spinal cord stimulation, injection of local anesthetics, and pharmacotherapy with potent anti-inflammatory and/or analgesic (pain-relieving) medications. The best approach to chronic pain management follows the Bio-Psycho-Social (BPS) model of care, in which an interdisciplinary team of healthcare providers assesses and treats the patient. The BPS model addresses the physical, psychological, and social components of chronic pain. The interdisciplinary team usually includes medical pain specialists (MDs specializing in pain management or anesthesiologists with a pain management fellowship), DCs, and/or Physical Therapists, Occupational Therapists, Psychotherapists, and Licensed Social Workers. The patient section of the Practical Pain Management (PPM) website provides useful information on effective treatments and self-management techniques to improve patients' functioning with chronic pain. Veritas Publication's Pain Management page offers unbiased, high-quality resources for patient education, empowering people to make informed health decisions.
PAIN RELIEF AS A HUMAN RIGHT
Roughly 80% of the global population lacks adequate access to basic pain treatment. High-income regions like North America and Europe consume the vast majority of available global opioids (such as morphine), leaving low- and middle-income countries with severe shortages due to restrictive laws and supply barriers. Studies show that chronic pain care and access to adequate analgesia frequently suffer from systemic biases, disproportionately affecting women, racial and ethnic minorities, rural populations, and low-income individuals. As a result, access to pain management as a human right has gained increasing currency in recent years. International frameworks, including World Health Organization (WHO) guidelines and United Nations standards, view effective pain relief and palliative care as core components of the universal right to health. The United Nations and regional human rights bodies have accepted the idea and incorporated it into key human rights reports, reviews, and standards. Medical organizations like IASP emphasize that failing to treat pain is a breach of medical ethics and professional responsibility. In countries like the United States, a historical push to treat pain as the "fifth vital sign" collided with a devastating opioid epidemic. Subsequent regulatory crackdowns and fear of prescribing have sometimes swung too far, leading to the undertreatment or abandonment of patients with chronic pain. While patients have a right to proper assessment and ethical care, human rights frameworks and medical consensus note that a "right to pain management" does not guarantee total or instantaneous elimination of all pain, as not all chronic pain is best managed solely through pharmacological intervention. Modern approaches emphasize balancing compassionate, evidence-based pain relief with multi-modal strategies, non-opioid therapies, mental health support, and safe addiction-care safeguards.
The Declaration of Montréal, adopted on September 3, 2010, at the first International Pain Summit in Montréal, Canada, is a landmark global document that recognizes access to pain management as a fundamental human right. It declares that access to pain management is a fundamental human right. Developed by IASP alongside delegates from 84 countries, the declaration addresses widespread, inadequate treatment of acute and chronic pain, noting that acute pain management is insufficient for over 50% of people in developed nations and up to 90% in developing nations. It highlights gaps such as professional knowledge deficits, social stigma, lack of national pain policies, and severe restrictions or lack of access to controlled pain medications, affecting roughly 5 billion people worldwide. The declaration calls on governments and healthcare institutions to establish supportive policies, laws, and infrastructure to prioritize and integrate pain care into healthcare systems. It also emphasizes healthcare professionals' obligation to provide competent, evidence-based, and compassionate pain assessment and management. Here is the link to the full text of the "Declaration that Access to Pain Management Is a Fundamental Human Right" in PDF format.
Create Your Own Website With Webador